On March 11, 2020, The Lancet Respiratory Medicine published a commentary entitled “Are Patients With Hypertension and Diabetes at Increased Risk for COVID-19 Infection?”
The authors pointed out that the patients with severe COVID-19 were likely to have hypertension and diabetes. They then explained that the virus uses its spike proteins to attach to angiotensin-converting enzyme 2 (ACE2), which is expressed by lung epithelial cells, which is how the virus gets into the lungs, where it replicates.
ACE inhibitors and angiotensin receptor blockers (ARBs) cause upregulation of ACE2, and the commentators state, “consequently, the increased expression of ACE2 would facilitate infection with COVID-19. We therefore hypothesise that diabetes and hypertension treatment with ACE2-stimulating drugs increases the risk of developing severe and fatal COVID-19.”
• The first DEATH of COVID-19 has been reported amongst an 83-year-old Female.
• 527 confirmed cases of COVID-19 have been reported in the Maldives – 507 active cases.
• 12 cases of local transmission outside of Male’ City was found in Shaviyani Atoll (north) which is
linked to a positive case.
• 1547 People are in Quarantine and 452 in isolation facilities across Maldives.
• 8327 samples have been tested, 8064 tested negative and results for 151 samples are pending.
This statement is a hypothesis and completely unsubstantiated; but, of course, some people read it as factual. Then they go on to say, “Based on a PubMed search on Feb 28, 2020, we did not find any evidence to suggest that antihypertensive calcium channel blockers increased ACE2 expression or activity, therefore these could be a suitable alternative treatment in these patients.”
The commentators went from an hypothesis all the way to a recommendation of stopping ACE inhibitors and ARBs within a one-page document. They did not present any data that COVID-19 patients taking ACE inhibitors or ARBs had worse outcomes. They also did not discuss the consequences of stopping the drugs, which could lead to increased cardiovascular events, worsening of heart failure, and renal complications.
Interestingly, other researchers have pointed out that there is a soluble version of ACE2, which is not on the cell membrane and which could act as a decoy for the virus to bind to and so the lung cells would be spared.1 This would mean that an increase in soluble ACE2 might be protective, and, if ACE inhibitors and ARBs increase soluble ACE2, then they may actually be beneficial. Now, we don’t know if the soluble ACE2 can even get to the virus considering that the virus is coming in from the airway side; however, if there is soluble ACE2 in the fluid layer just on top of the lung cells, the drugs might have a protective effect.
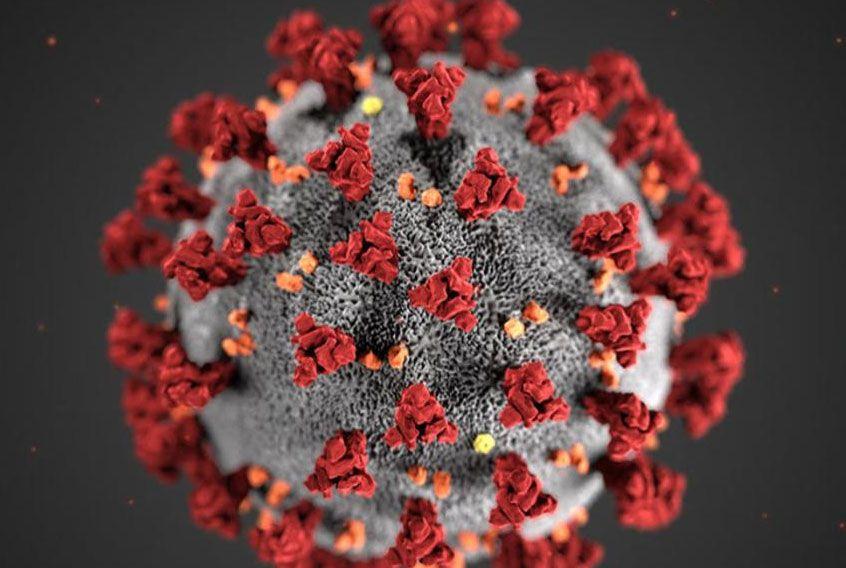
The world has seen the emergence of a Novel Corona Virus on 31 December 2019, officially referred to as COVID-19. The virus was first isolated from persons with pneumonia in Wuhan city, China.
The virus can cause a range of symptoms, from ranging from mild illness to pneumonia. Symptoms of the disease are fever, cough, sore throat and headaches. In severe cases difficulty in breathing and deaths can occur.
There is no specific treatment for people who are sick with Coronavirus, and no vaccine to prevent the disease.
Considering the current situation and spread of the disease globally, the Director General of WHO declared the outbreak to be a public health emergency of international concern PHEIC.
The Emergency Committee has provided advice to WHO, the People’s Republic of China, all countries, and to the global community on measures to control this outbreak. Member states such as Maldives are focusing to detect cases imported in the country and limit more infection from these cases.
Other research has shown that angiotensin II is needed for lung fibrosis to occur.2 COVID-19 and SARS patients who recovered had excessive scaring of their lungs. In animal models, when there is no angiotensin II, the scarring does not happen. ACE2 breaks down angiotensin II, and less angiotensin II might mean less fibrosis. So, if ACE inhibitors and ARBs increase ACE2, the effect could be protective against lung fibrosis and further damage.
The SARS virus used ACE2 as its entry point as well,3 and we never saw detrimental effects of being on ACE inhibitors or ARBs during the SARS epidemic.
I cite all these different studies and facts to point out that there are many aspects that we need to consider and that that oversimplification is not always wise.
That is why the American Heart Association, the Heart Failure Society of America, and the American College of Cardiology put out a statement on March 17, 2020. The three organizations recommend, “continuation of angiotensin converting enzyme inhibitors (ACE-i) or angiotensin receptor blocker (ARB) medications for all patients already prescribed for indications such as heart failure, hypertension or ischemic heart disease.”
They go on to say, “we have reviewed the latest research – the evidence does not confirm the need to discontinue ACE-i or ARBs, and we strongly recommend all physicians to consider the individual needs of each patient before making any changes to ACE-i or ARB treatment regimens….” They concluded by saying, “these recommendations will be adjusted as needed to correspond with the latest research.”
Think of a patient who has COVID-19. The virus has already gained entry into the cell, so stopping the ACE inhibitor or ARB would not reduce the COVID-19 risk but it would increase the cardiovascular and renal risk. Keeping the patient on therapy makes sense. Now, think of your patients who not infected with COVID-19. Stopping their drugs would put them at high risk of cardiovascular and renal complications, and, if they never get COVID-19, their risk would have been heightened for no reason.
This all means, basically, that we should keep our patients on their ACE inhibitors or ARBs. One caveat is that, if they are dehydrated, vomiting, or have diarrhea, then we should be thinking about holding the drugs; otherwise…
We can protect our patients from COVID-19 by encouraging them to protect their personal borders through social distancing; however, we should let the ACE inhibitors and ARBs do their job at protecting their cardiovascular and renal systems.
References
Batlle D, Wysocki J, Satchell K. Soluble angiotensin-converting enzyme 2: a potential approach for coronavirus infection therapy? Clin Sci (Lond). 2020;134(5):543-545. https://portlandpress.com/clinsci/article-lookup/doi/10.1042/CS20200163
Meng Y, Yu CH, Li W, et al. Angiotensin-converting enzyme 2/angiotensin-(1-7)/Mas axis protects against lung fibrosis by inhibiting the MAPK/NF-κB pathway. Am J Respir Cell Mol Biol. 2014 Apr;50(4):723-736. https://www.atsjournals.org/doi/full/10.1165/rcmb.2012-0451OC?url_ver=Z39.88-2003&rfr_id=ori:rid:crossref.org&rfr_dat=cr_pub%3dpubmed
Jia HP, Look DC, Shi L, et al. ACE2 receptor expression and severe acute respiratory syndrome coronavirus infection depend on differentiation of human airway epithelia. J Virol. 2005;79(23):14614-14621. https://jvi.asm.org/content/79/23/14614.long